Scoring Methodology
This page sets out, item by item, how Legit.Health quantifies the components of the CLASI, from a single-region photograph through to an aggregated Activity and Damage score. It also sets out the two ways the platform supports the CLA-IGA-R, the investigator's global assessment used alongside CLASI in current CLE trials: capturing the investigator's grade, and estimating items from the visible signs the device measures.
The CLASI instrument
The CLASI (Cutaneous Lupus Erythematosus Disease Area and Severity Index) scores the skin in 13 anatomical regions, each assessed independently and summed without area weighting.
Anatomical regions
| Group | Regions |
|---|---|
| Head | Scalp; ears; nose, including the malar area; rest of the face |
| Neck | V-area of the neck; posterior neck and shoulders |
| Trunk | Chest; abdomen; back and buttocks |
| Limbs | Arms; hands; legs; feet |
Two further items are scored on the scalp by quadrant, and two are answered once per patient rather than per region.
Within a region, each item is scored on the most severely affected lesion for that item. The published form instructs the rater to select the score in each anatomical location that describes the most severely affected cutaneous lupus-associated lesion, and the original paper scores each area according to the worst affected lesion within it for each symptom. The worst erythema and the worst dyspigmentation of a region can therefore sit on different lesions. The instrument records neither the number of lesions nor the area they cover.
CLASI Activity
| Item | Type | Scale | Scored |
|---|---|---|---|
| Erythema | Ordinal | 0–3 | Each of the 13 regions |
| Scale and hypertrophy | Ordinal | 0–2 | Each of the 13 regions |
| Non-scarring alopecia | Ordinal | 0–3 | Scalp, by quadrant |
| Recent hair loss | Binary | 0–1 | Once per patient |
| Mucous membrane lesions | Binary | 0–1 | Once per patient |
The erythema scale runs from absent, through faint pink and red, to dark red or violaceous. Scale and hypertrophy distinguishes absent, scaling, and verrucous or hypertrophic change. The Activity score ranges from 0 to 70.
CLASI Damage
| Item | Type | Scale | Scored |
|---|---|---|---|
| Dyspigmentation | Binary | 0–1 | Each of the 13 regions |
| Scarring, atrophy and panniculitis | Ordinal | 0–2 | The 12 regions other than the scalp |
| Scalp scarring | Ordinal | 0, 3, 4, 5, 6 | Scalp, by quadrant |
Scarring on the scalp is not scored with the other regions but by quadrant: 0 when absent, 3 for one scarred quadrant, then one point more for each further quadrant, up to 6 when the whole scalp is scarred. A single scarred quadrant therefore already outweighs the highest scarring score of any other region, which is 2.
The dyspigmentation subtotal is doubled when dyspigmentation in that patient usually lasts at least 12 months after active lesions have resolved, reported by the patient, a history question rather than an observation. The Damage score ranges from 0 to 56.
The two scoring formulas
The activity score sums the two activity signs across the scored anatomical regions and adds the three items that are not observations of a single region:
where is erythema (0–3) and scale or hypertrophy (0–2) in region , is mucous-membrane involvement (0–1), recent hair loss (0–1) and non-scarring alopecia (0–3).
The damage score sums dyspigmentation and scarring, with the dyspigmentation subtotal doubled by the persistence flag :
where is dyspigmentation (0–1), is 1 when dyspigmentation usually lasts at least twelve months, is scarring or atrophy (0–2) in each region other than the scalp, and is scalp scarring. The factor is how the formula writes the doubling: it leaves the dyspigmentation subtotal unchanged when and doubles it when . The device measures the imaged terms; the clinician supplies , and .
The CLA-IGA-R instrument
The CLA-IGA-R (Cutaneous Lupus Activity Investigator's Global Assessment, Revised) is an investigator's global assessment of CLE activity, used as an efficacy endpoint in current CLE trials. Where CLASI sums per-region items into a score, the CLA-IGA-R asks the investigator for one judgement that considers all of the patient's active lesions together, recorded as three separate items rather than a single combined grade. A patient with one bright red plaque on the face and several faint pink lesions on the arms receives, under CLASI, a separate erythema score for each region, which are then summed; under the CLA-IGA-R, the same patient receives one erythema grade for the disease as a whole.
| Item | Covers | Scale |
|---|---|---|
| Erythema | Redness of active lesions | 0–4 |
| Other morphologic characteristics (OMC) | The three characteristics below, graded together | 0–4 |
| Edema or infiltration | Swelling or firm thickening of the lesions | Part of OMC |
| Scale | Scale on the lesion surface | Part of OMC |
| Secondary change | Erosion, crusting and vesicles | Part of OMC |
| Follicular activity | Hair follicle involvement, assessed through follicular plugging | 0–4 |
Each item uses the same five-point scale: 0 clear, 1 almost clear, 2 mild, 3 moderate and 4 severe. OMC is one grade, not three: the investigator considers edema or infiltration, scale and secondary change together and records a single 0–4 value. The published scoring instructions for the original CLA-IGA describe which characteristics to consider, and that not all of them need to be present, but give no formula for combining them. Trials typically report responder endpoints per item, for example the proportion of patients reaching an erythema score of 0 or 1. The revised instrument's inter- and intra-rater reliability has been studied by Merola and colleagues (2025); the reference is on the Publications page.
Two ways to record the CLA-IGA-R
The platform supports the CLA-IGA-R in two distinct ways, and they produce different kinds of value. Only one of them is the investigator's assessment, so a protocol states which applies to each item.
| Investigator input | Estimate from measured signs | |
|---|---|---|
| What it is | The investigator's grade per item, recorded as a structured entry | A per-item value derived from the visible signs the device measures |
| Source | The investigator's examination of the patient | The visit's photographs |
| Items covered | Erythema, other morphologic characteristics and follicular activity | Erythema in full; OMC except erosion and vesicles |
| Status | The CLA-IGA-R as the instrument defines it | Exploratory until characterised against investigator grading |
Capturing investigator input
The investigator grades each of the three items at the review step, on the instrument's 0–4 scale, and the platform records the grades as structured entries attached to the patient and the visit, in the same way as the CLASI components answered outside the image. The grades are exported per visit alongside the measured signs. At the moment of grading, the measured values and segmentation overlays for that visit are available to the investigator as an objective reference, which supports the judgement without substituting for it.
Follicular activity, and the erosion and vesicles within OMC, can only be recorded this way.
Estimating from automatically measured visible signs
For the items built from signs the device measures, the platform derives a per-item estimate from the visit's photographs:
- Erythema: from erythema intensity, with erythema extent reported alongside, both measured as described below.
- Other morphologic characteristics: from several measured signs, each reported as its own value. Induration and desquamation are the two measurements that resolve the CLASI scale and hypertrophy item; swelling and crusting are among the secondary signs the device grades for atopic dermatitis. By characteristic:
- Edema or infiltration: induration intensity and swelling intensity, reported as two values.
- Scale and crusting: one value. The device grades scale and crusting together as a single measurement, so it counts once in the estimate rather than once for each.
- Erosion and vesicles: no estimate. Neither is measured, so both remain investigator input.
- Follicular activity: no estimate. The device does not measure follicular plugging or hyperkeratosis. As with the CLASI alopecia items, hair loss percentage is reported alongside the investigator's grade as a related continuous scalp measure, not as an estimate of the item, since hair loss is a downstream effect of follicular activity rather than the activity itself.
Turning per-image values into one value per item is configuration work, specified during study setup and recorded in the study configuration, as for CLASI:
- Scale mapping: each sign value is mapped from its source instrument onto the CLA-IGA-R 0–4 item scale, as described under scale alignment.
- Combination within OMC: the rule that resolves the measured values into a single OMC value. The instrument does not define one, so it is agreed with the sponsor during study setup. The individual values are reported alongside the combined one.
- Aggregation across lesions: the CLA-IGA-R gives one grade for all of the patient's lesions together rather than one per region, while the device returns one value per photograph. The published instructions for the original CLA-IGA state that the severity of each feature is averaged over all of the patient's lesions, without regard to extent, and the estimate applies the same averaging to the per-image values. How it is applied, for instance how a lesion photographed in more than one frame is counted, is fixed in the study configuration before the first patient is imaged.
The estimate is reported alongside the investigator's grade, not in place of it. How closely it reproduces investigator grading in a CLE cohort has not been studied, which is set out on the limitations page.
How the device quantifies each component
Every measurement below is produced from one photograph of one anatomical region. The device returns per-sign values together with pixel-level segmentation masks and a DIQA image quality score.
Erythema
Erythema is the dominant contributor to CLASI Activity, and it is scored by judging colour by eye against a four-point verbal scale. That combination, the heaviest item resolved by the least reproducible kind of judgement, is where automated measurement adds most.
The device returns two distinct quantities from the same photograph. Erythema intensity is a graded severity value, the direct analogue of the CLASI 0–3 item. Erythema extent is the erythematous area, derived from a pixel-level segmentation mask and reported either relative to the photographed area or as an absolute area in square millimetres, as described under lesion area below.
CLASI itself grades intensity only and ignores extent within a region, which is a known coarseness of the instrument: a region with a single small plaque and a region that is confluently involved score identically. The extent figure is therefore reported alongside the CLASI-aligned intensity value rather than folded into it, giving a continuous secondary measure with more resolution than the four-point item, without altering the CLASI arithmetic.
Scale and hypertrophy
CLASI combines two physically different findings into one 0–2 item: surface scaling at level 1, and verrucous or hypertrophic thickening at level 2. The device measures them as two independent signs, desquamation intensity for the scaling component and induration intensity for the thickening component, then resolves them into the single CLASI level. Because thickening dominates the item, a region with measurable induration resolves to level 2 regardless of the scaling value.
Measuring the two separately also preserves information the instrument discards. In a study of hypertrophic or verrucous CLE, the induration trend on its own is a more sensitive response measure than the combined 0–2 item.
Dyspigmentation
CLASI records dyspigmentation as a single present-or-absent item per region, covering both loss and excess of pigment. The device measures the depigmented component as a continuous extent, from its own segmentation mask, reported relative to the photographed region or as an absolute area.
Post-inflammatory hyperpigmentation is not quantified as a separate measurement. In practice this means the CLASI-D dyspigmentation item is satisfied by the measured depigmentation where depigmentation is present, and remains a clinician judgement where the pigmentary change is hyperpigmentation alone. The distinction matters in CLE, where the two carry different prognostic weight, and it is set out in full on the limitations page.
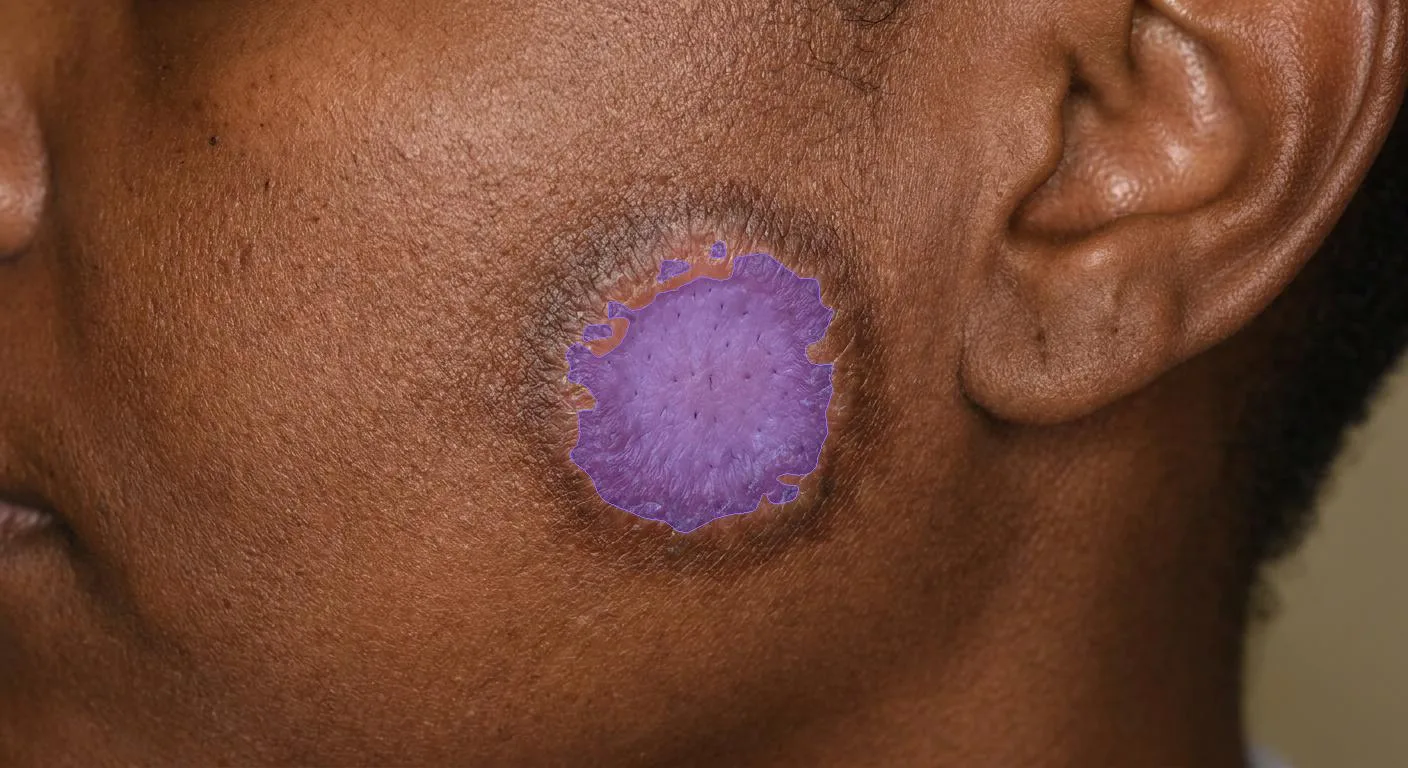
The depigmentation mask is confined to the pale centre and excludes the surrounding hyperpigmented border. Synthetic image, real device output.
Repigmentation as a derived measure
The CLASI-D item is binary, and the Damage score is constructed to accumulate. Neither property allows the instrument to represent partial repigmentation, where a depigmented plaque refills from its periphery inward over successive visits. Under CLASI-D that lesion holds the same value until it crosses the threshold at which the item flips, and then moves by one point.
A continuous hypopigmentation extent has no such step. The reduction in hypopigmented area from baseline is directly reportable per lesion and per region, at whatever resolution the imaging supports, and it is reported as an exploratory measure alongside the CLASI-D item rather than as a modification of it. Because erythema is measured by a separate model, a repigmenting lesion that is still mildly inflamed does not confound the pigmentation figure.
Lesion area and the physical size reference
Every extent measurement starts as a count of segmented pixels, and a pixel count becomes a clinical quantity in one of two ways.
Relative extent divides the segmented pixels by the pixels of the photographed region. It requires nothing but the photograph. It is also a ratio whose denominator is set by how the photograph was framed, so it is comparable only between images captured at the same distance and angle. A closer capture at a later visit shrinks the denominator and inflates the measurement with no clinical change behind it, which makes relative extent a sound descriptive measure and an unreliable longitudinal one.
Relative extent is the segmented sign area over the photographed region area:
Absolute area converts the segmented pixel count into square millimetres using a marker of known side (mm) spanning pixels in the same frame:
The device performs this camera calibration against the marker and reports area independent of working distance. Change from baseline is then a change in the lesion, not in how close the camera was.
| Relative extent | Absolute area | |
|---|---|---|
| Requires | Nothing beyond the photograph | A calibration marker in frame |
| Unit | Proportion of the photographed area | Square millimetres |
| Sensitive to framing | Yes | No |
| Suitable for change from baseline | Only under fixed framing | Yes |
| Typical use | Descriptive, feasibility, retrospective sets | Endpoints, longitudinal analysis |
For any CLE study where lesion extent, pigmentation or repigmentation is an endpoint rather than a description, capture with markers and report absolute area. Marker specifications and placement are on the calibration markers page.
Target lesion measurement
CLE protocols commonly designate one or more target lesions, representative lesions identified at baseline and assessed at every subsequent visit. This is a lesion-level design running alongside the region-level CLASI, and it exists because a single well-characterised lesion tracks treatment response with far less noise than a whole-body sum.
For each designated target lesion the device reports area, erythema intensity, desquamation and induration intensity, and depigmentation extent, at every visit where it is captured. Reported as absolute area, these form a per-lesion trajectory that is independent of how many regions were photographed at that visit.
Target lesions are identified by a stable per-lesion identifier assigned at baseline and carried in the image metadata. Physical markers placed on the skin at capture, where a protocol uses them, are an aid to the photographer and to the reviewer; they are not what binds a measurement to a lesion across visits, and a protocol should not rely on them for that.
Alopecia and scalp involvement
The device measures hair loss percentage, the proportion of the scalp showing hair loss, from scalp photography.
This measures the extent of hair loss. CLASI instead scores its pattern: whether loss is diffuse, focal in one quadrant, or focal in more than one quadrant. The two are related but not interchangeable, so hair loss percentage is reported as a continuous scalp measure alongside, rather than in place of, the clinician's CLASI alopecia grade. The same figure informs both the Activity alopecia item and the Damage scalp scarring item; CLASI separates scarring from non-scarring alopecia and the measurement does not. Both points are detailed on the limitations page.
Diagnosis support
Independently of severity scoring, the device returns a ranked differential diagnosis with associated risk indicators. Cutaneous lupus erythematosus is among the conditions it recognises. In a CLE trial this serves screening and eligibility review rather than the endpoint itself.
Components answered outside the image
Three CLASI components are not observations of photographed skin and are collected through the platform as structured clinician or patient entries, then combined with the measured items:
Mucous membrane lesions (CLASI-A, 0–1): an oral and nasal mucosal examination, outside the scope of the skin photography protocol.
Recent hair loss (CLASI-A, 0–1): whether the patient has noticed hair loss in the preceding 30 days, a history question with no visual correlate at a single timepoint.
Dyspigmentation duration (CLASI-D multiplier): whether dyspigmentation in that patient usually lasts at least 12 months after active lesions have resolved, as reported by the patient, a history question that doubles the dyspigmentation subtotal.
Scale alignment
A sign name alone does not identify a measurement. The same clinical sign is scored on different scales by different validated instruments, and the device returns each sign on the scale of the scoring system that produced it. An erythema value graded 0 to 3 under one instrument is not the same quantity as an erythema value graded 0 to 4 under another, even though both are called erythema.
Every sign read for a CLE study is therefore qualified by its source instrument and mapped explicitly onto the CLASI item scale during study configuration. The mapping is fixed for the duration of the study and recorded in the study configuration, so that a value reported at the final visit means exactly what the same value meant at baseline. Treating an unqualified sign value as interchangeable across instruments is the most consequential integration error available in this architecture, and the explicit mapping exists to prevent it. The same applies to a CLA-IGA-R estimate, where each sign is mapped onto the 0–4 item scale instead.
From per-image values to a CLASI score
Aggregation runs in four steps.
- Quality gate: each image is assessed by DIQA before any sign is read. Images below the quality threshold are rejected for recapture and never contribute a value.
- Per-image sign measurement: the device returns intensity and extent values for the signs present in that photograph, with a confidence figure per sign.
- Region assignment: each image contributes to the CLASI region it was captured for. Regions photographed in more than one frame are consolidated to a single per-region value by taking the highest value of each item, because the instrument scores the most severely affected lesion.
- Score assembly: region values, quadrant scalp items and the clinician-entered components are combined into CLASI-A and CLASI-D, with the dyspigmentation multiplier applied.
Step 3 is the one that fails silently. If an image is not attached to a patient, a visit and a named region, steps 1 and 2 still succeed and return perfectly valid per-image values, while step 4 becomes impossible. The result is a dataset of measurements that cannot be assembled into the endpoint the study was designed around. The imaging protocol page specifies the metadata that prevents this.
Manual compared with automated assessment
| Aspect | Manual assessment | Automated components |
|---|---|---|
| Erythema grading | Visual colour judgement, four-point scale | Measured intensity, plus continuous extent |
| Scale and hypertrophy | Combined 0–2 judgement | Desquamation and induration measured separately |
| Dyspigmentation | Present or absent per region | Continuous depigmentation extent |
| Activity versus damage | Rater separates them by judgement | Measured by distinct models |
| Global assessment (CLA-IGA-R) | One judgement per item for all lesions together | Investigator grade captured per item; erythema and part of OMC estimated from measured signs |
| Reproducibility | Varies between and within raters | Identical values for an identical image |
| Time per assessment | Over fifty judgements per visit | <2 seconds per image |
| Site calibration | Rater training and calibration exercises | None; the measurement is the same everywhere |
The practical consequence for a trial is the reduction of measurement noise in the endpoint, which is what determines how large a treatment effect a given sample size can detect. The consequence for a long study is that a damage score accumulated over several years remains comparable with its own baseline even when the rater who recorded that baseline has left the site.