Scoring Methodology
The platform from Legit.Health scores acne from the two things a dermatologist's overall impression rests on: how many inflammatory lesions there are, and how closely they cluster. The software detects every inflammatory lesion on each photograph, measures how densely the lesions cluster and combines both into a continuous score on the IGA scale and into ALADIN (Acne Lesion And Density INdex), the same score on a finer 0 to 10 scale, and the investigator reviews the report at the visit.
The example images on this page are synthetic dermatology imagery used for illustration; they are not patient records.
- Photograph: Two diagonal views of the face, one for each half.
- Detect: Every inflammatory lesion located and marked.
- Count: The number of detections, .
- Measure density: How closely the lesions cluster, .
- Score: An IGA score from 0 to 4, and ALADIN from 0 to 10.
Inflammatory lesion detection
A deep learning object detection model (YOLOv11-M) finds each inflammatory lesion on the photograph and draws a box around it. It was trained to detect inflammatory lesions as a single class: papules, pustules and nodules are counted together and not told apart, because distinguishing lesion subtypes on a photograph is a well-known source of disagreement between raters (Medela et al., 2026). Comedones (blackheads and whiteheads), which are noninflammatory, are not counted.
Each detection carries a confidence score, and detections below a fixed threshold are discarded; the threshold is the same for every image and every site.
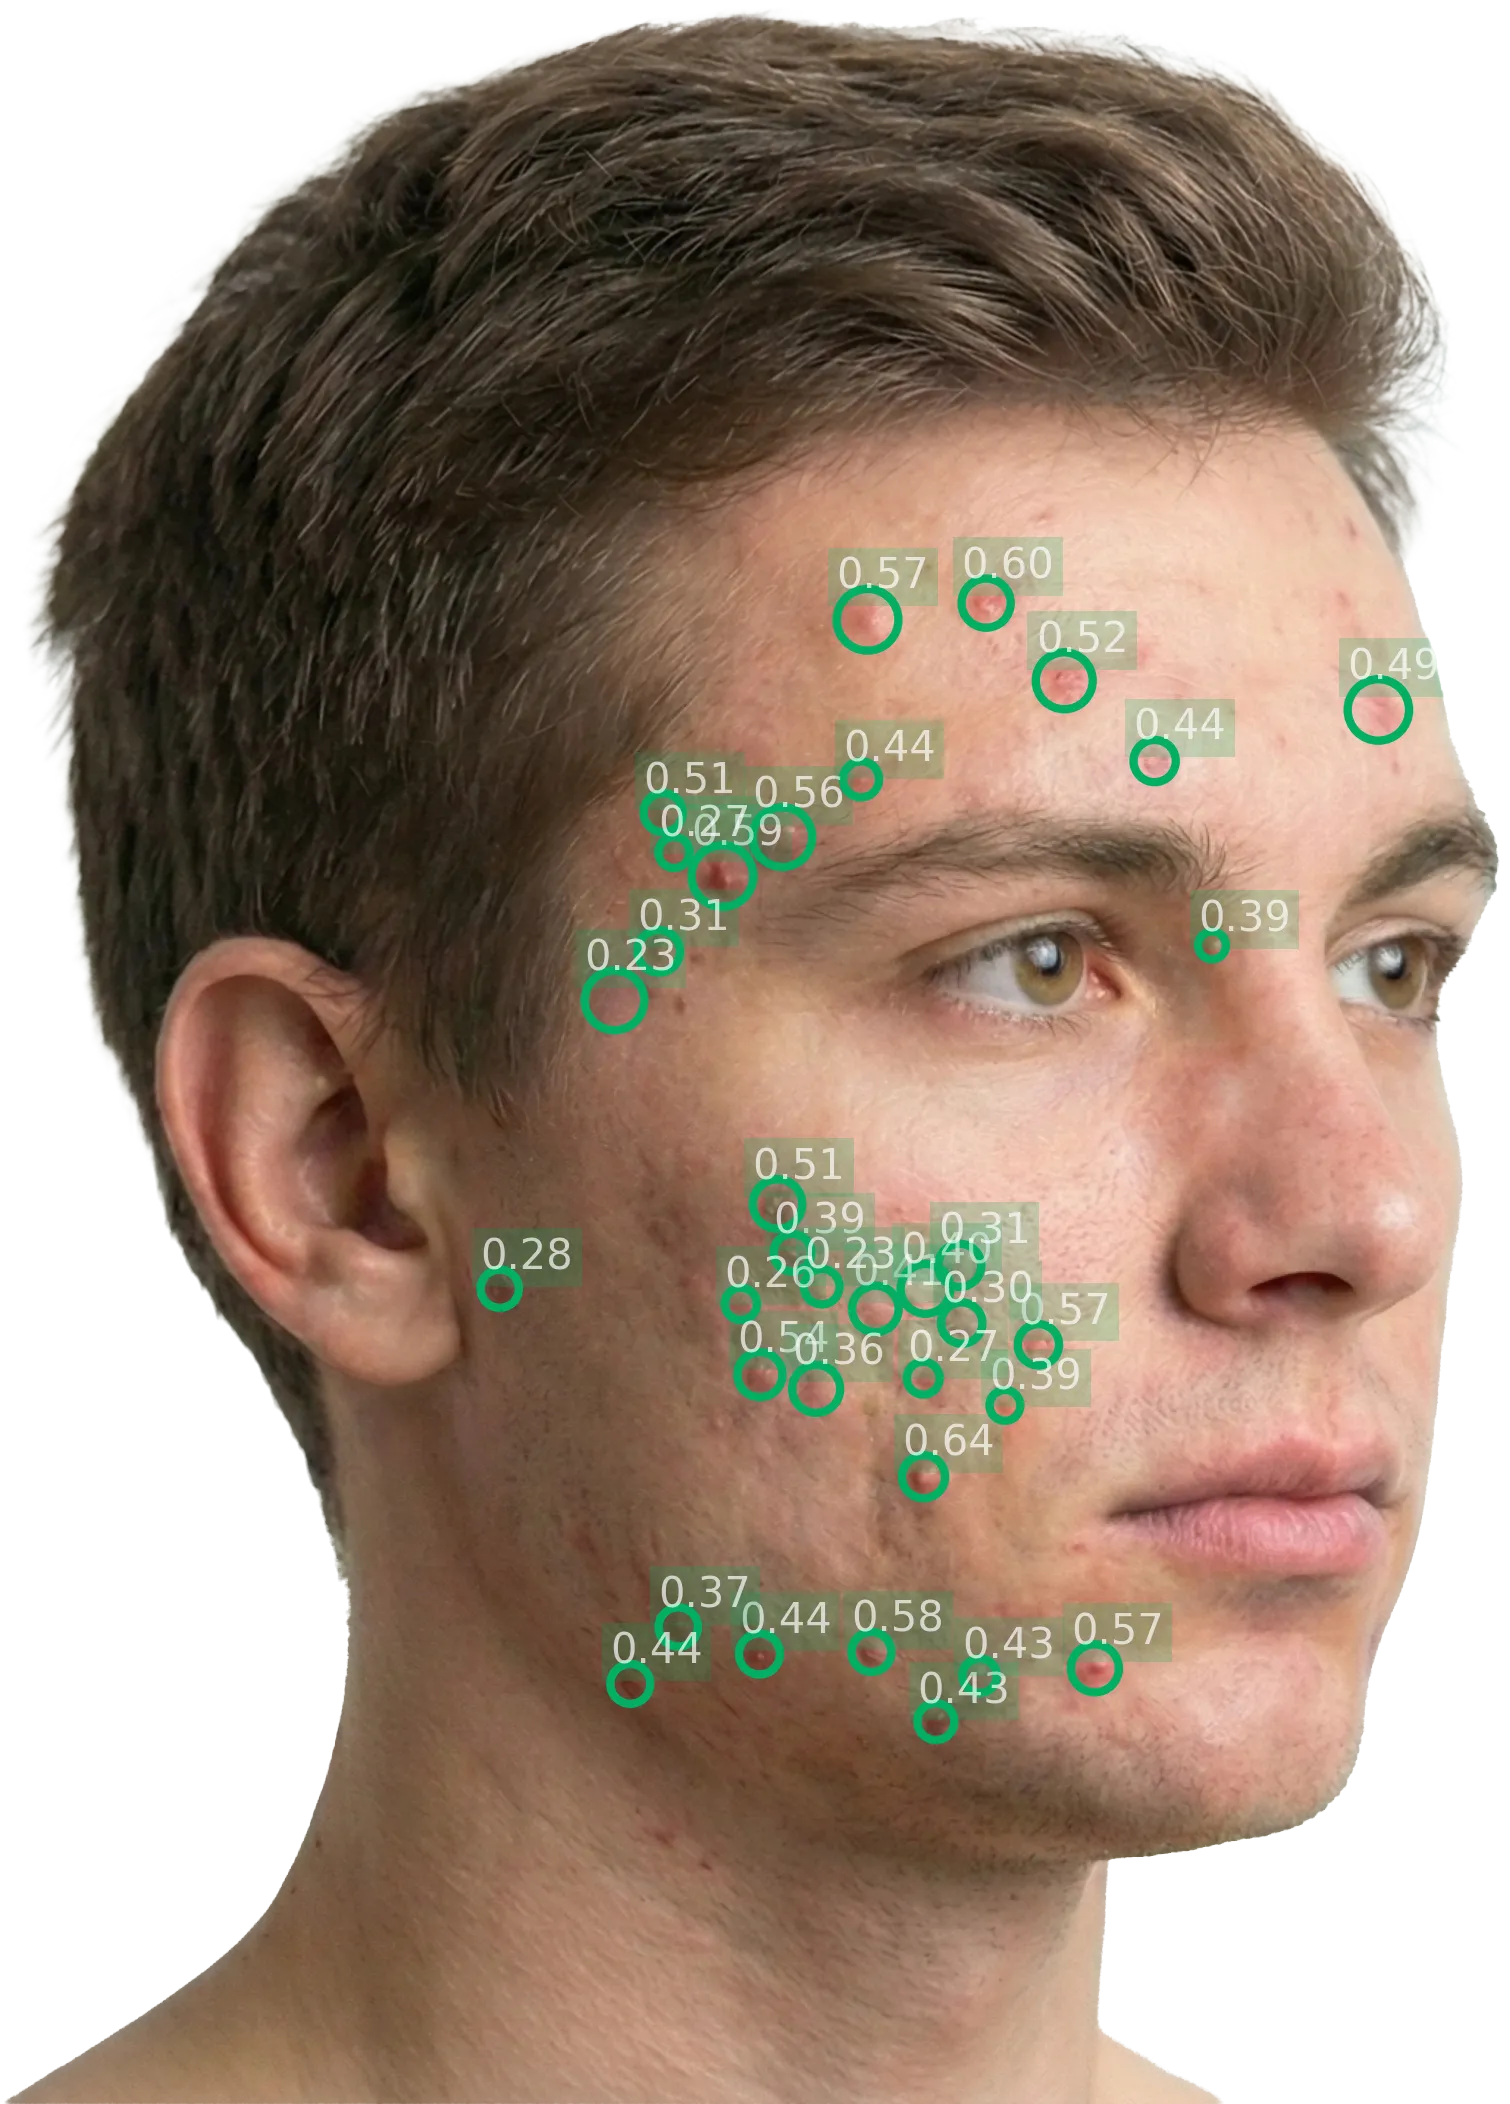
Left diagonal: 36 lesions detected

Right diagonal: 35 lesions detected
The number next to each lesion is the model's confidence in that detection.
Spatial density
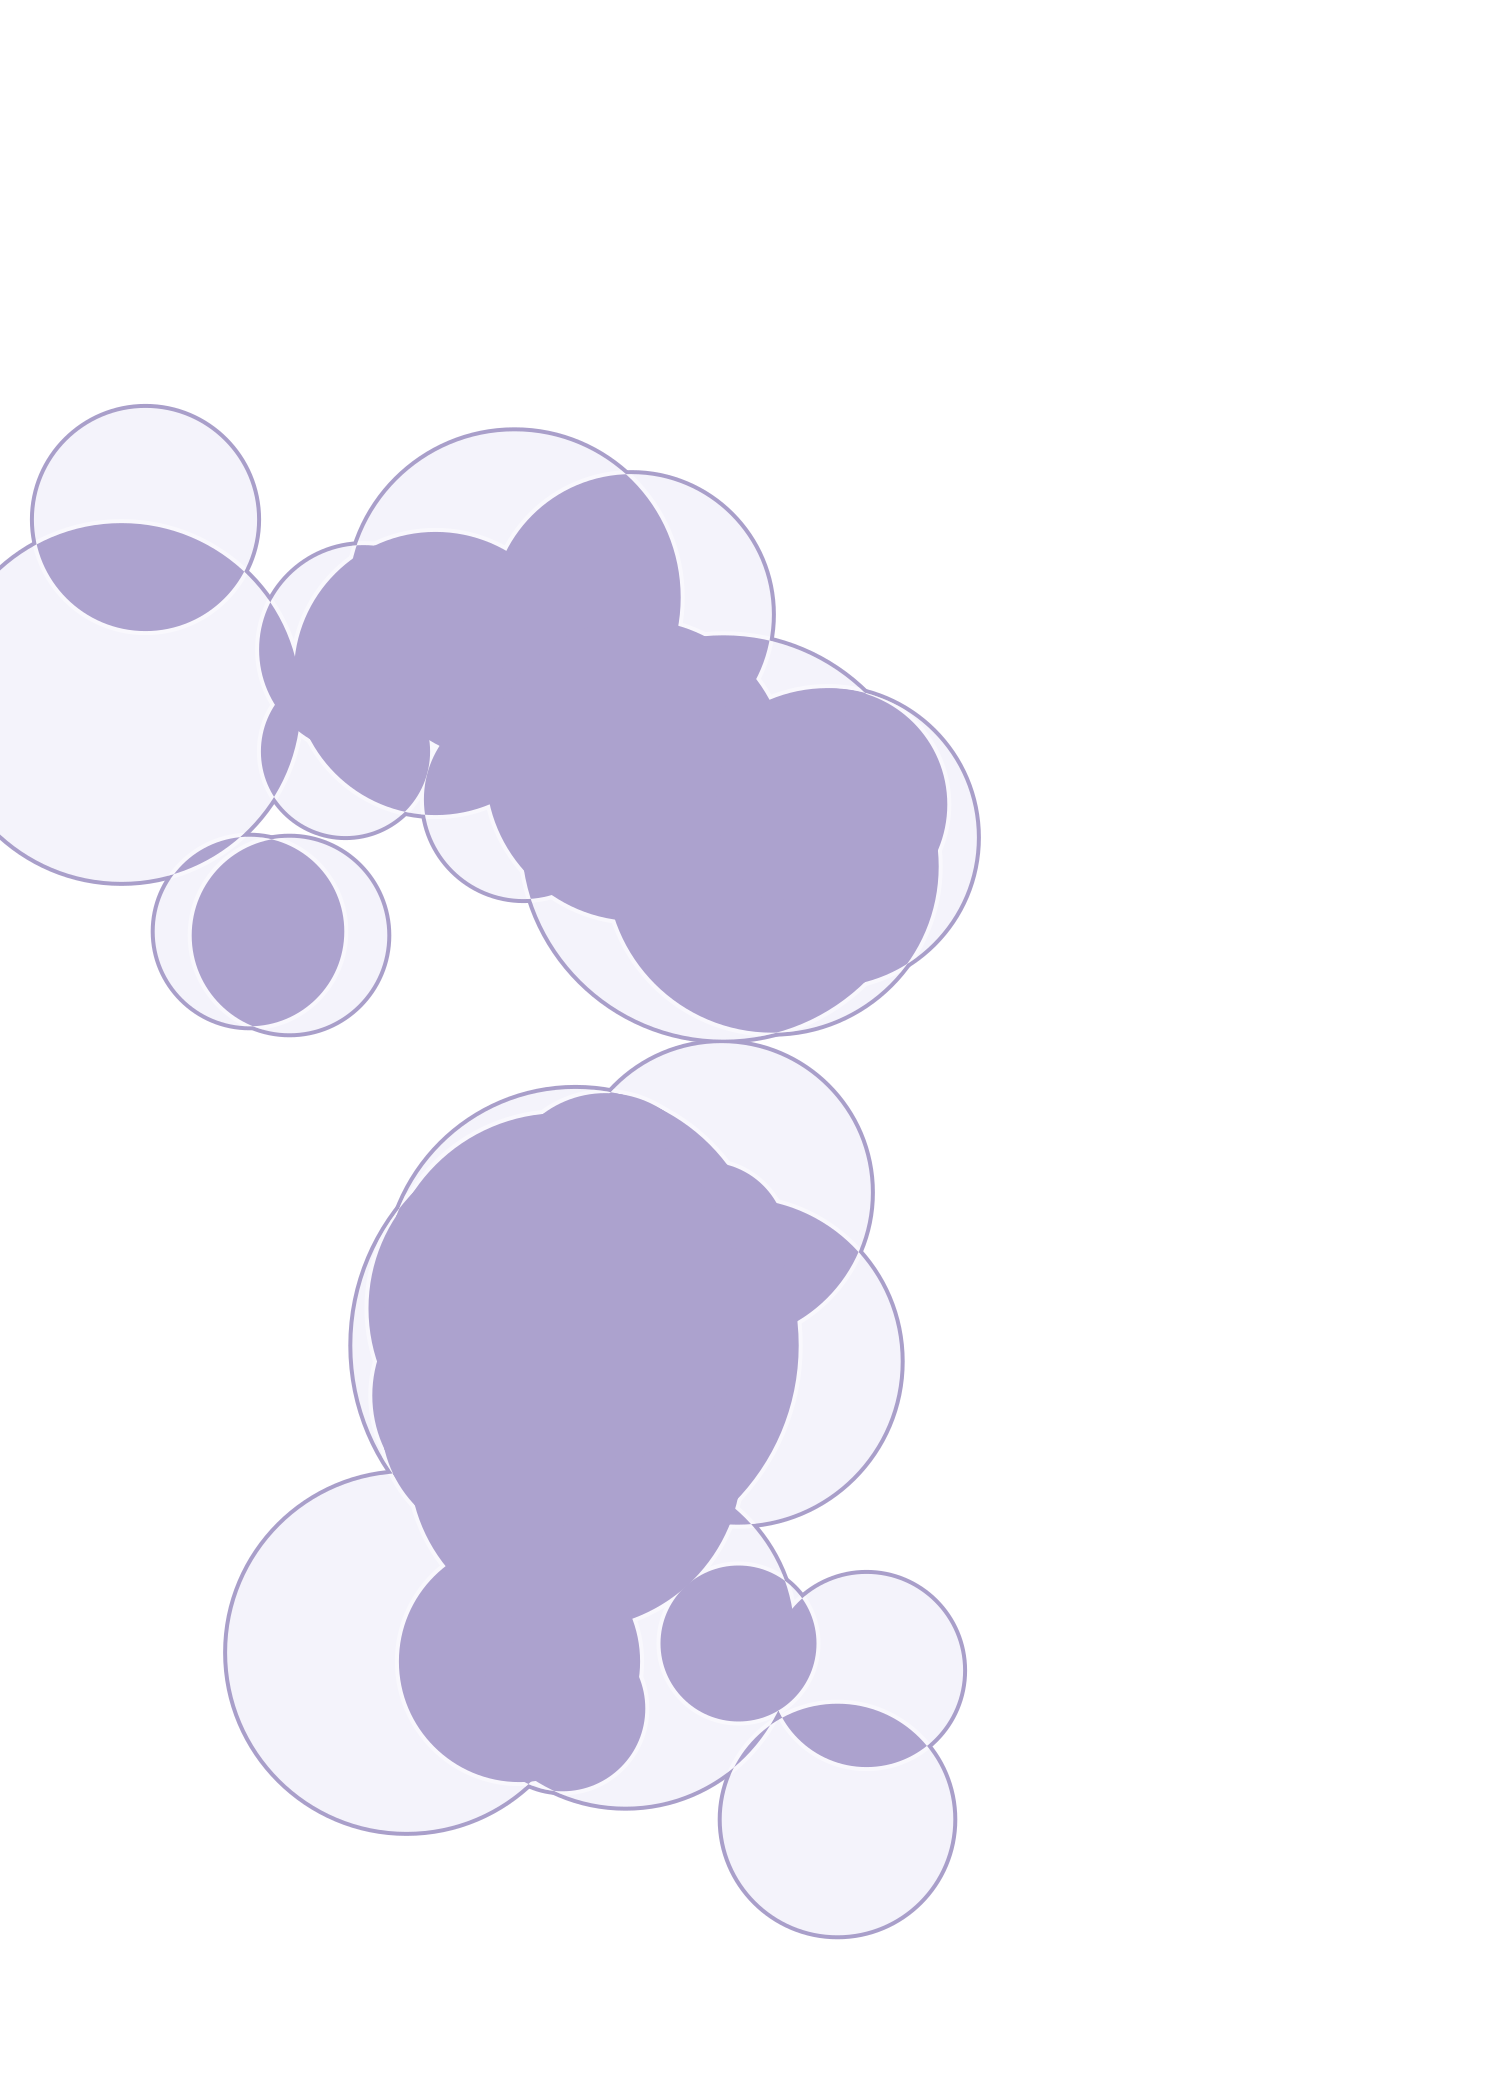
Lesions can be scattered across the face or packed into one area, and a count alone does not tell the two apart (Medela et al., 2026). The density score does:
Each detection becomes a circle, its radius enlarged six times so that nearby lesions touch. is the area covered by any circle and the part covered by two or more, darker in the image. runs from 0, scattered lesions, to close to 1, confluent ones.
ALADIN
The method combines the lesion count and the density in one formula, which gives a score on the scale of the IGA:
where and are constants. The formula and its constants were derived by symbolic regression and differential evolution, choosing the expression that best agreed (Cohen's kappa with quadratic weights) with the consensus IGA of three expert dermatologists on the AcneSeverity-V1 dataset, while staying simple enough to read. The score grows with both the number of lesions and their density, and is clipped to the range 0 to 4, the range of the IGA (Medela et al., 2026).
ALADIN is the same score on a 0 to 10 scale, which gives finer granularity for following a patient between visits:
Unlike the investigator's IGA, which takes whole grades, both scores are continuous, so they keep the intermediate values between two grades. The publication calls the 0 to 4 score itself ALADIN, and reports its results on that scale.
The same continuous score on two scales: ALADIN (0 to 10) above, the IGA score (0 to 4) below.
The IGA scale
The FDA guidance recommends an IGA on an ordinal scale of about five grades reported in whole numbers, and the wording that defines each grade differs between the IGA versions in use (Bae et al., 2024); the study protocol fixes which one applies.
Multi-perspective protocols and overlap handling
Counting methodology
The standard protocol follows the Hayashi Criterion (Hayashi et al. (2008)), which grades acne severity by counting inflammatory eruptions per half-face. Images are captured at approximately 70-degree diagonal angles, one from the left and one from the right. The AI lesion counting is consistent with this methodology: each perspective corresponds to approximately one half-face.
| Hayashi Criterion grade | Range |
|---|---|
| Mild | 0–5 lesions per half-face |
| Moderate | 6–20 lesions per half-face |
| Severe | 21–50 lesions per half-face |
| Very severe | >50 lesions per half-face |
The AI lesion counting is consistent with this methodology: each perspective corresponds to approximately one half-face, and the per-perspective count maps naturally to the grading thresholds.
Overlap between views
Each diagonal photograph is scored on its own, with its own lesion count, density and IGA score, and the score for the visit is the mean of the two half-face scores. The two views meet in the middle of the face, around the nose, the centre of the forehead and the chin, where a lesion can appear in both photographs. Because the visit score is an average of the two views rather than a sum, a lesion seen in both does not inflate it; lesion counts are reported per view for the same reason.
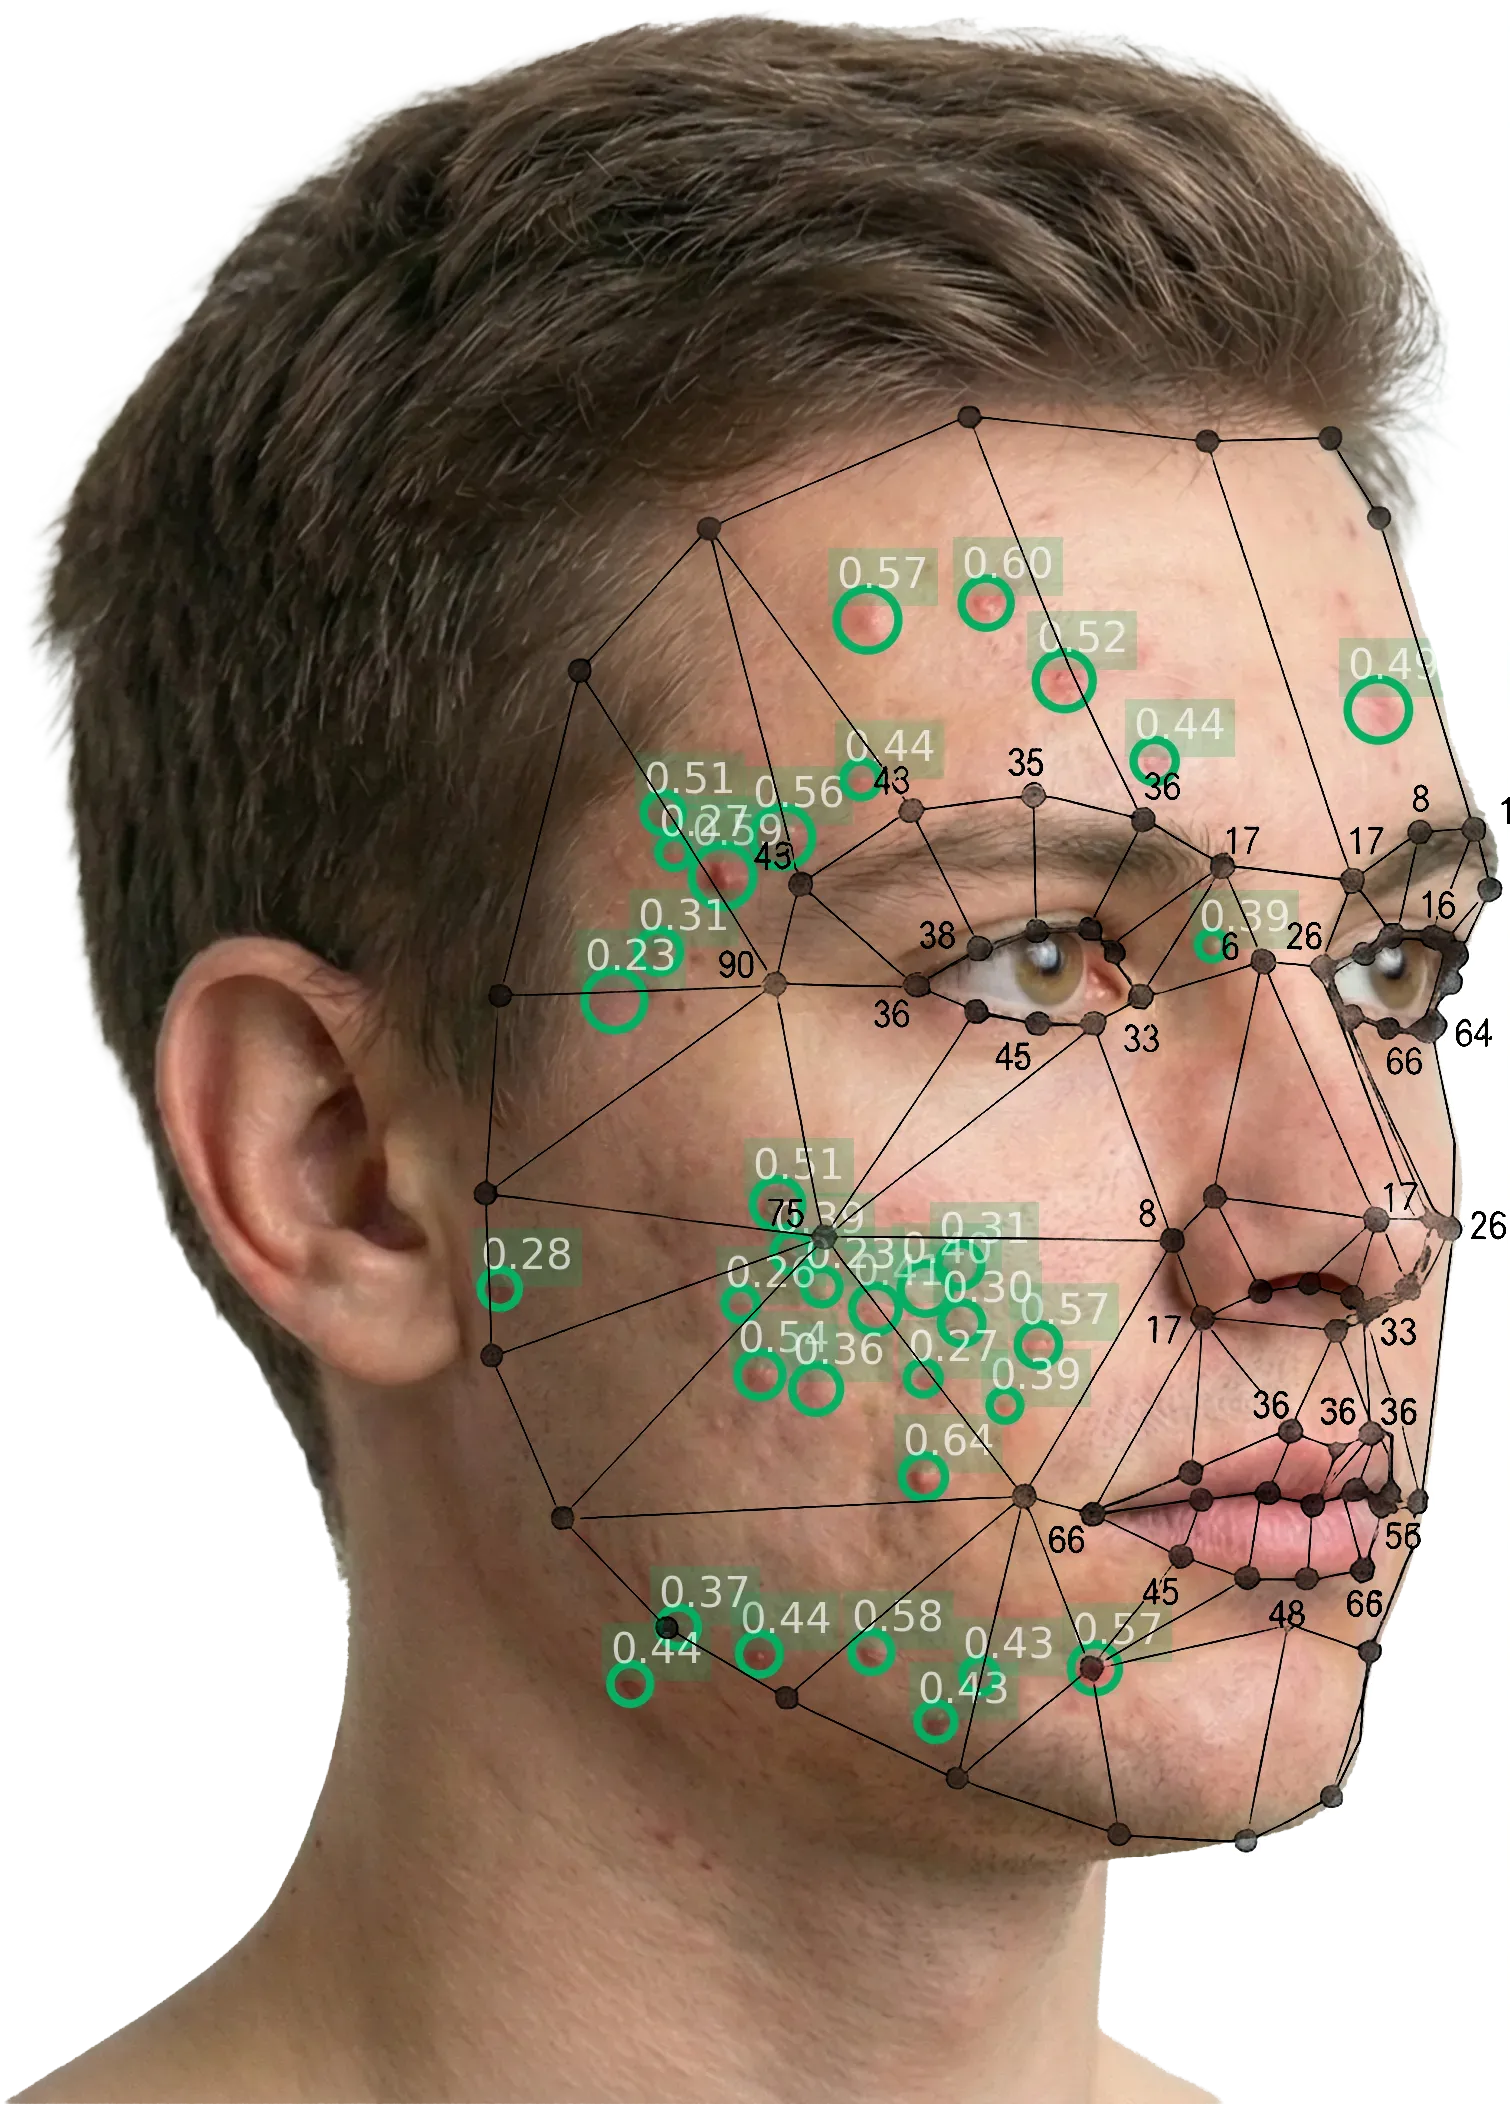
The facial regions covered by the left diagonal view, with the lesions detected in them.
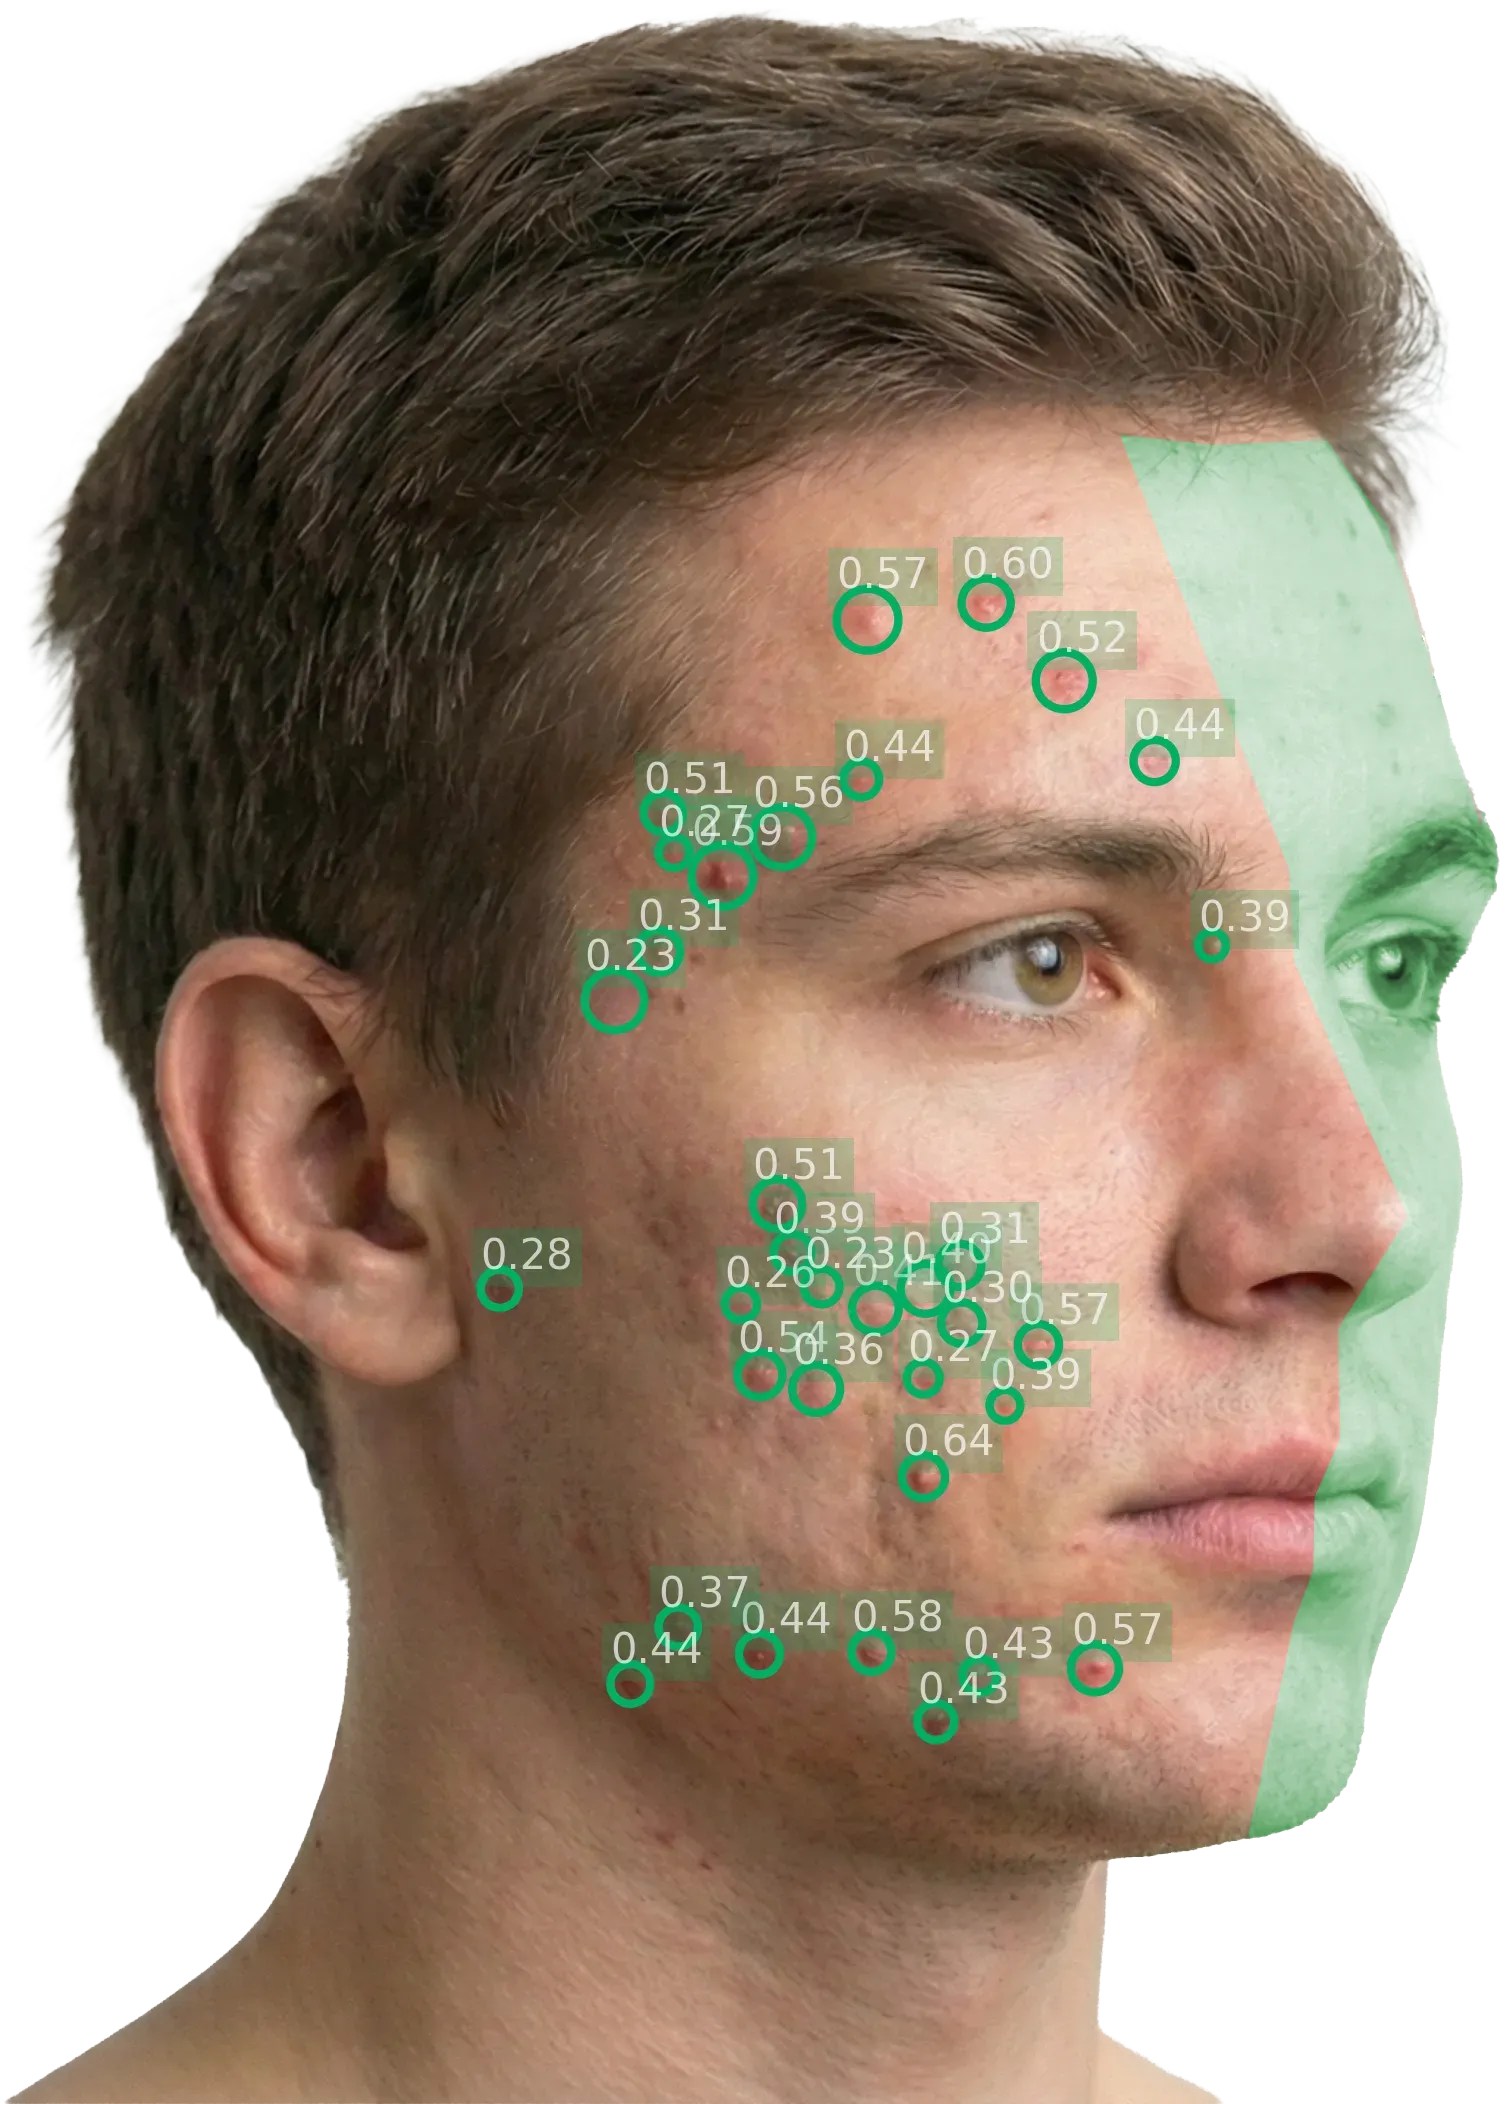
Left diagonal: the green area is the side of the face that the right diagonal view captures best.
Response definitions
Each visit is scored on its own. Response to treatment is read against the patient's baseline visit, as the FDA guidance defines it:
- IGA success: the patient is clear or almost clear (grade 0 or 1) and has improved by at least two grades from baseline.
- Change in lesion count: the absolute and the percentage change in the inflammatory lesion count from baseline.
Because both are reported at every visit on the same scale, these definitions come straight from the per-visit results, with no re-scoring.
A worked example
An illustrative example, not study data: one patient followed across a 12-week study, with both diagonal photographs taken at every visit. L and R are the left and right diagonal views. The visit score is the mean of the two half-face IGA scores, ALADIN is that score times 2.5, and the IGA grade is the visit score rounded to the nearest grade, for this example.
ALADIN by visit
The visit score on the 0 to 10 scale, against the five IGA grades
Lesion count by view
Inflammatory lesions on each half of the face
| Visit | IGA score | ALADIN | IGA grade | Lesions (L / R) | IGA success |
|---|---|---|---|---|---|
| Baseline | 3.13 | 7.8 | 3 (Moderate) | 36 / 35 | Reference |
| Week 4 | 2.40 | 6.0 | 2 (Mild) | 24 / 22-33% / -37% | Not yet |
| Week 8 | 1.62 | 4.1 | 2 (Mild) | 15 / 13-58% / -63% | Not yet |
| Week 12 | 0.80 | 2.0 | 1 (Almost clear) | 6 / 5-83% / -86% | Achieved |
At week 12 the patient is almost clear, two grades below baseline, so the visit meets the definition of IGA success. Between weeks 4 and 8 the whole grade does not change, while ALADIN falls from 6.0 to 4.1 and the lesion count by more than a third: the continuous score shows the improvement that the whole grade hides. In a trial, these results sit alongside the investigator's own IGA as supportive, objective data.
Manual vs. automated scoring
Manual scoring
Lesions counted and IGA graded by a clinician
- Lesion count: Counted by eye at the visit
- Severity grade: IGA judged on broad descriptors such as "some" or "many"
- Resolution: Whole grades
- Reproducibility: Depends on the rater and varies across sites
- Traceability: The count is a number, not a record of each lesion
- Training: Calibration exercises to align raters
- Time per assessment: Grows with lesion burden: every lesion on the face found and counted
Automated scoring
AI detection on two photographs, reviewed by the investigator
- Lesion count: Counted on each photograph, every lesion marked
- Severity grade: A continuous IGA score computed from count and density, and ALADIN on a 0 to 10 scale
- Resolution: Continuous scores, 0 to 4 and 0 to 10
- Reproducibility: Same score for the same image, every time
- Traceability: Every counted lesion is visible on the report
- Training: Following the capture protocol instead of calibrating judgements
- Time per assessment: Seconds of AI analysis, plus capture of two photographs
The model version is locked at study initiation, so every patient is scored by the same model from first visit to last; see model version locking. The validation of the method is on Clinical evidence.
The AI counts what the photograph shows. Lesions hidden by hair, make-up or the camera angle are not counted, lesion types are not told apart, and on faces with very little acne the detector can find lesions that dermatologists would not count. See Limitations.